
Search
Subscribe to daily UMEM Pearls (FREE!) via:
Using MRI, patient self assessment and a neural network, 157 brain injured patients were evaluated for their predicted brain age vs their actual brain age over the course of 18 months. These 157 patients showed older (less healthy) brain age compared to their actual age.
Further evidence that traumatic brain injury has long term structural, functional and neurocognitive effects.
Show References
Bottom line: Implementing an eCPR program does not harm non-eCPR cardiac arrest patients — and may improve their outcomes, particularly with hands on training.
Show Additional Information
Show References
Bottom line: You must consider vitamin K deficiency bleeding in neonates, and be prepared to treat
IM Vitamin K refusal is on the rise in neonates - now up to 1 in 20 infants will not receive vitamin K with as many as 1 in 60 patients who did not receive the injection having some form of clinical bleeding.
Bleeding can present as early (<24h), classic (2-7 days), or late (up to 6 months) so consider this in any bruising, bleeding, hematemesis, melena, or infants with irritability, vomiting or fussiness with concern for intracranial bleeding.
Patients who received oral vitamin K who present with bleeding should be presumed to be vitamin K deficient.
There is no pattern of bleeding/bruising/ICH that suggests Vitamin K deficiency over other bleeding disorders or trauma.
prolonged PT and INR suggest Vitamin K deficiency.
Bleeding should be treated based on severity
- mild to moderate bleeding, or plan for operative/procedural interventions - give IV vitamin K
- severe bleeding- treat bleeding with transfusions as needed, give IV vitamin K, give FFP or 4 factor PCC
When giving IV vitamin K there is a risk of anaphylaxis so the patient should be monitored, though there is no evidence for use of any pre-medication.
Show References
The anion gap (AG) represents the difference between measured cations and measured anions in the serum, reflecting the concentration of unmeasured anions.
A normal anion gap is typically 10–12 mmol/L, although reference ranges may vary.
AG = Sodium - (Chloride + Bicarb)
An elevated anion gap generally suggests an underlying metabolic acidosis due to the accumulation of unmeasured anions.
There are several situations that can affect the interpretation and calculation of the anion gap:
1. Correct for albumin.
- A patient's expected normal anion gap can be approximated as:
Normal AG = serum albumin × 3 (albumin in g/dL).
2. Use the measured sodium, not corrected sodium.
- When calculating the anion gap, use the measured sodium concentration rather than the corrected sodium concentration.
3. Common causes of a low anion gap (AG less than 3 mmol/L):
- Laboratory error (most common)
- Hypoalbuminemia
- Electrolyte derangements: hyperkalemia, hypercalcemia, and hypermagnesemia
- Monoclonal gammopathies (e.g., multiple myeloma)
- Bromide-containing medications:
- Pyridostigmine
- Ipratropium/tiotropium
- Dextromethorphan
- Rocuronium
- Lithium toxicity
- Salicylate poisoning (with certain laboratory assays)
- Iodide exposure
Show Additional Information
Show References
You can look for aortic stenosis quickly with qualitative and quantitative evaluation using POCUS:
Qualitatively
- Obtain a parasternal long axis or short axis at the level of the base of the heart (Mercedes-Benz sign).
- Evaluate the aortic valve leaflets
- Is there calcifications?
- Are the leaflets mobile?
- Is there also LV hypertrophy
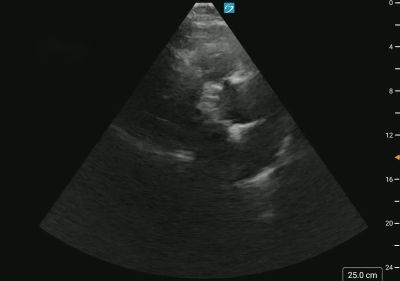
- Image shows a parasternal long axis view with thickened aortic valve leaflets and poor leaflet movement.
Quantitatively
- Obtain an apical 5 chamber view in cardiac mode
- Place the pulse wave doppler gate just at the LVOT and trace the LVOT VTI
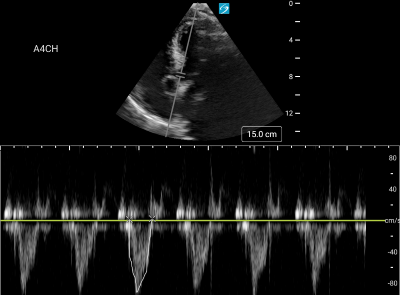
- Then place the continuous wave doppler gate inside the aortic valve and trace the aortic valve VTI.
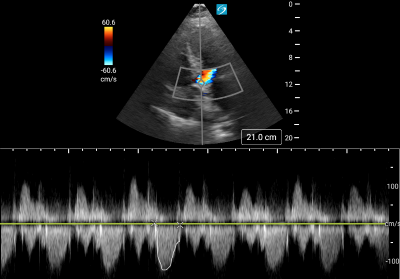
- Calculate the dimensionless index = LVOT VTI/AV VTI
- Normal 1:1 ratio
- Mild Stenosis 1:2 ratio
- Moderate Stenosis 1: 3 ratio
- Severe Stenosis 1 :4 ratio
There are some limitations with performing these measurements such as mitral regurgitation and LV hypertrophy can reduce the aortic velocity measurement, leading to underestimation of AS severity. The ultrasound beam also needs to be completely parallel to the flow and the measurement is flow dependent.
Show References
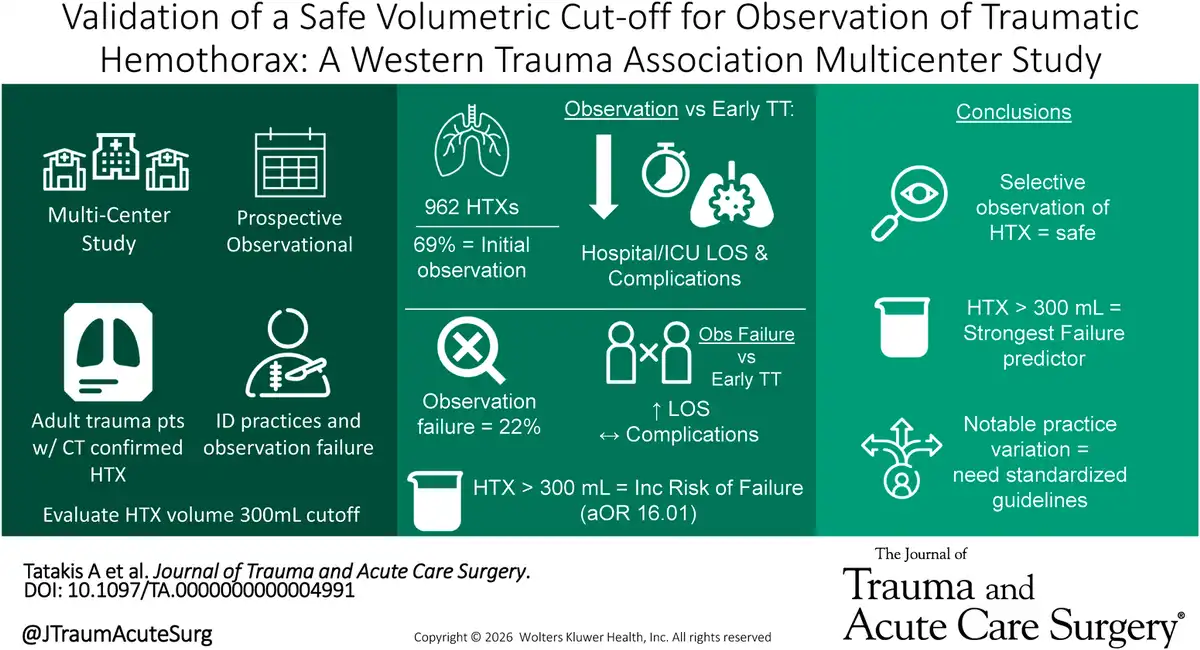
This prospective observational study says yes if it is less than 300 ml. (Calculated with Mergo’s formula of v=d2 xl).
See this pearl for a refresher on volume calculation
https://www.medschool.umaryland.edu/em/cme/umem-educational-pearls/?id=4862
Show References
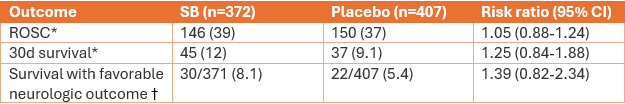
A recent RCT published in JAMA evaluated the use of sodium bicarbonate for in-hospital cardiac arrest and found no differences in rates of ROSC, 30-d survival, or survival with a favorable neurologic outcome. The sodium bicarbonate group had higher rates of adverse events such as alkalosis and hypernatremia.
Bottom line: Routine use of sodium bicarbonate during cardiac arrest is not recommended.
Show Additional Information
Show References
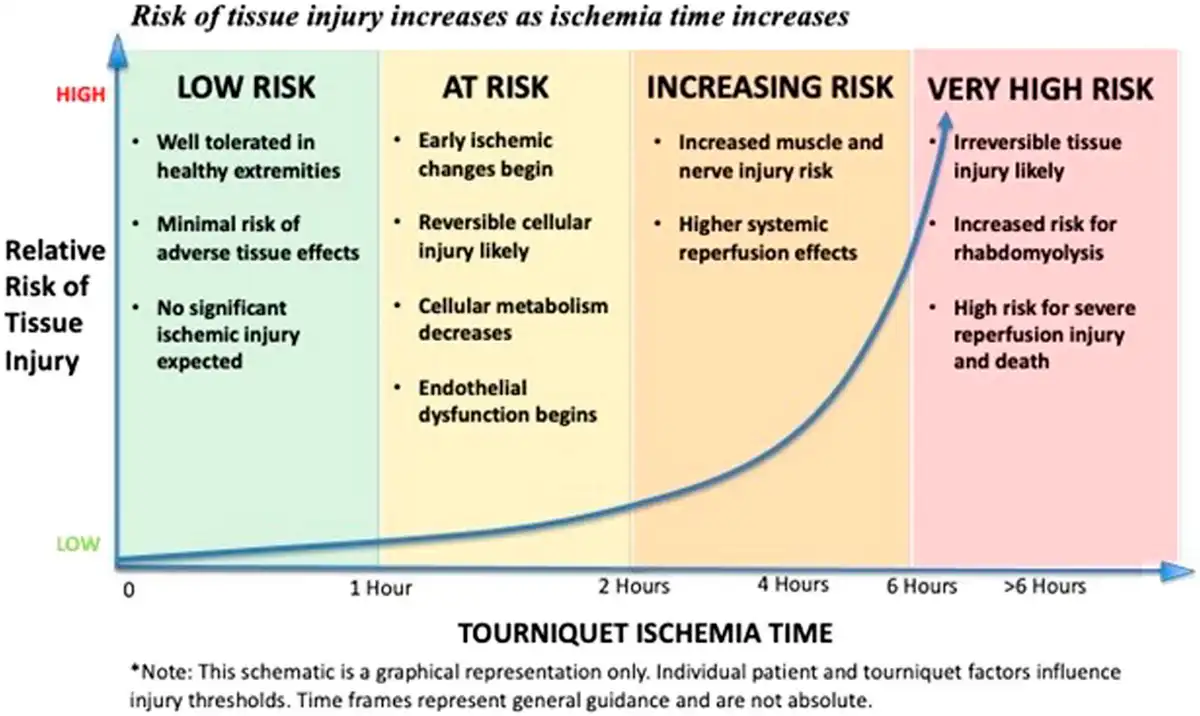
Tourniquets can be life saving. Studies do show they are often unnecessarily applied. Tourniquet time is associated with limb salvageability. For those that practice in an environment where immediate vascular or trauma surgery isn’t available, the ability to convert a tourniquet to a less restrictive process can be limb saving.
This review suggests: “tourniquet conversion requires a controlled, slow release (generally over 1–2 min, followed by at least 2 minutes of direct pressure to the wound with a moist dressing) to assess for ongoing hemorrhage while balancing the competing risks of rebleeding and reperfusion-associated complications. Conversion is generally recommended in patients who are hemodynamically stable, without traumatic amputation, and in whom the wound can be closely monitored for recurrent hemorrhage.”
Show References
Doesn’t really seem to be the question. This meta analysis found no benefit in treating asymptomatic (and no evidence of end organ dysfunction) hypertensive ED pts. There was a signal to harm in treating inpatients.
Show References
new AHA guidelines recommend changes to standard of care for pediatric severe airway foreign body obstructions
Show Additional Information
Show References
Rose and colleagues used a framework (Autor’s Framework) developed in labor economics to evaluate the work of the emergency physician and the potential for replacement by AI. Mapping emergency physician tasks to a four-quadrant grid, they found that most time on shift is spent in non-routine abstract or manual tasks, areas more protected from AI penetration.
Rose C, Molins E, Schoeffler A, Kabeer R, Frank MR, Preiksaitis C. Will Artificial Intelligence Replace Me? Automation Susceptibility of Emergency Physician Tasks; Annals of Emergency Medicine, 2026; 88, 551-561.
This study found no reason to decrease pregnant women’s dosing of medication for opiate use disorder. There was no increase in neonatal withdrawal with standard dosing vs decrease dosing.
As with most things, what is good for mom is good for baby. Keeping mom from relapsing to opiate use is the number one goal of MOUD.
Show References

45 year old male presents with nausea, vomiting, profuse diarrhea, and abdominal cramping occurring 6-7 hours after eating a meal he cooked containing wild mushrooms he picked the day before. What is you diagnosis?
Show Additional Information
Show References
Norepinephrine is widely viewed as the first line vasopressor for many types of shock, including undifferentiated shock and septic shock. But as the norepinephrine dose escalates, a perennial question is when to add a second agent, most commonly vasopressin. Based in part on trials like VASST and VANISH, a norepinephrine dose of roughly 0.1-0.2 mcg/kg/min is commonly cited as the time to add on vasopressin.
The VASSPR study was a cluster crossover randomized trial comparing lower (0.1 mcg/kg/min of norepinephrine) vs higher (0.4 mcg/kg/min of norepinephrine) threshold for initiation vasopressin in septic shock patients and was published in JAMA just a few weeks ago.
Bottom Line: This relatively large, high-quality study found no mortality benefit for initiating vasopressin when at a norepinephrine dose of 0.1 mcg/kg/min (or equivalent), which is a common practice, vs initiating vasopressin when at a norepinephrine dose of 0.4 mcg/kg/min. So whether you choose to stick with the current threshold of roughly 0.1-0.2 of norepi that many of us use as your queue to start a second agent, or wait a little later up to 0.4, that's a reasonable approach. Equipoise remains as to the benefit of adding a second agent and when it should be initiated. Of note, the surviving sepsis guidelines say 0.25-0.5 mcg/kg/min, so you also have support from those guidelines if you choose to wait.
Show References
Question
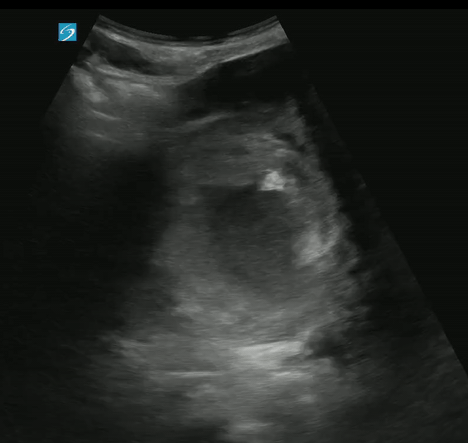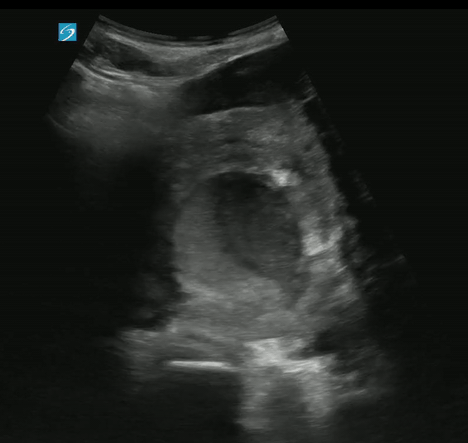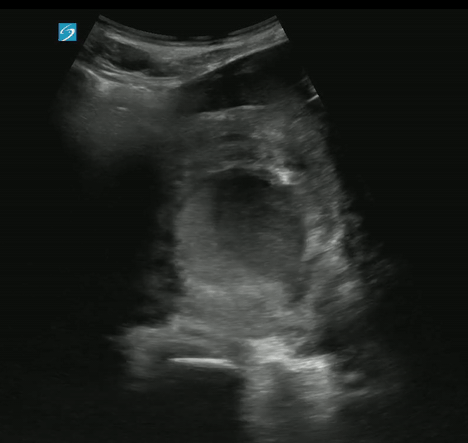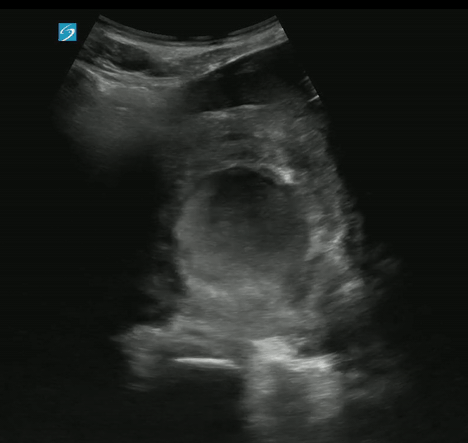
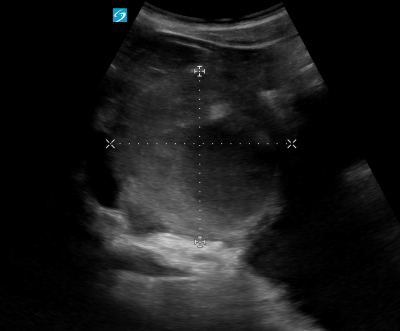
A male in his 70s presents to the emergency department after a syncopal episode with hypotension and abdominal pain.
What's the diagnosis? What's the correct measurement?
Show Answer
Show References
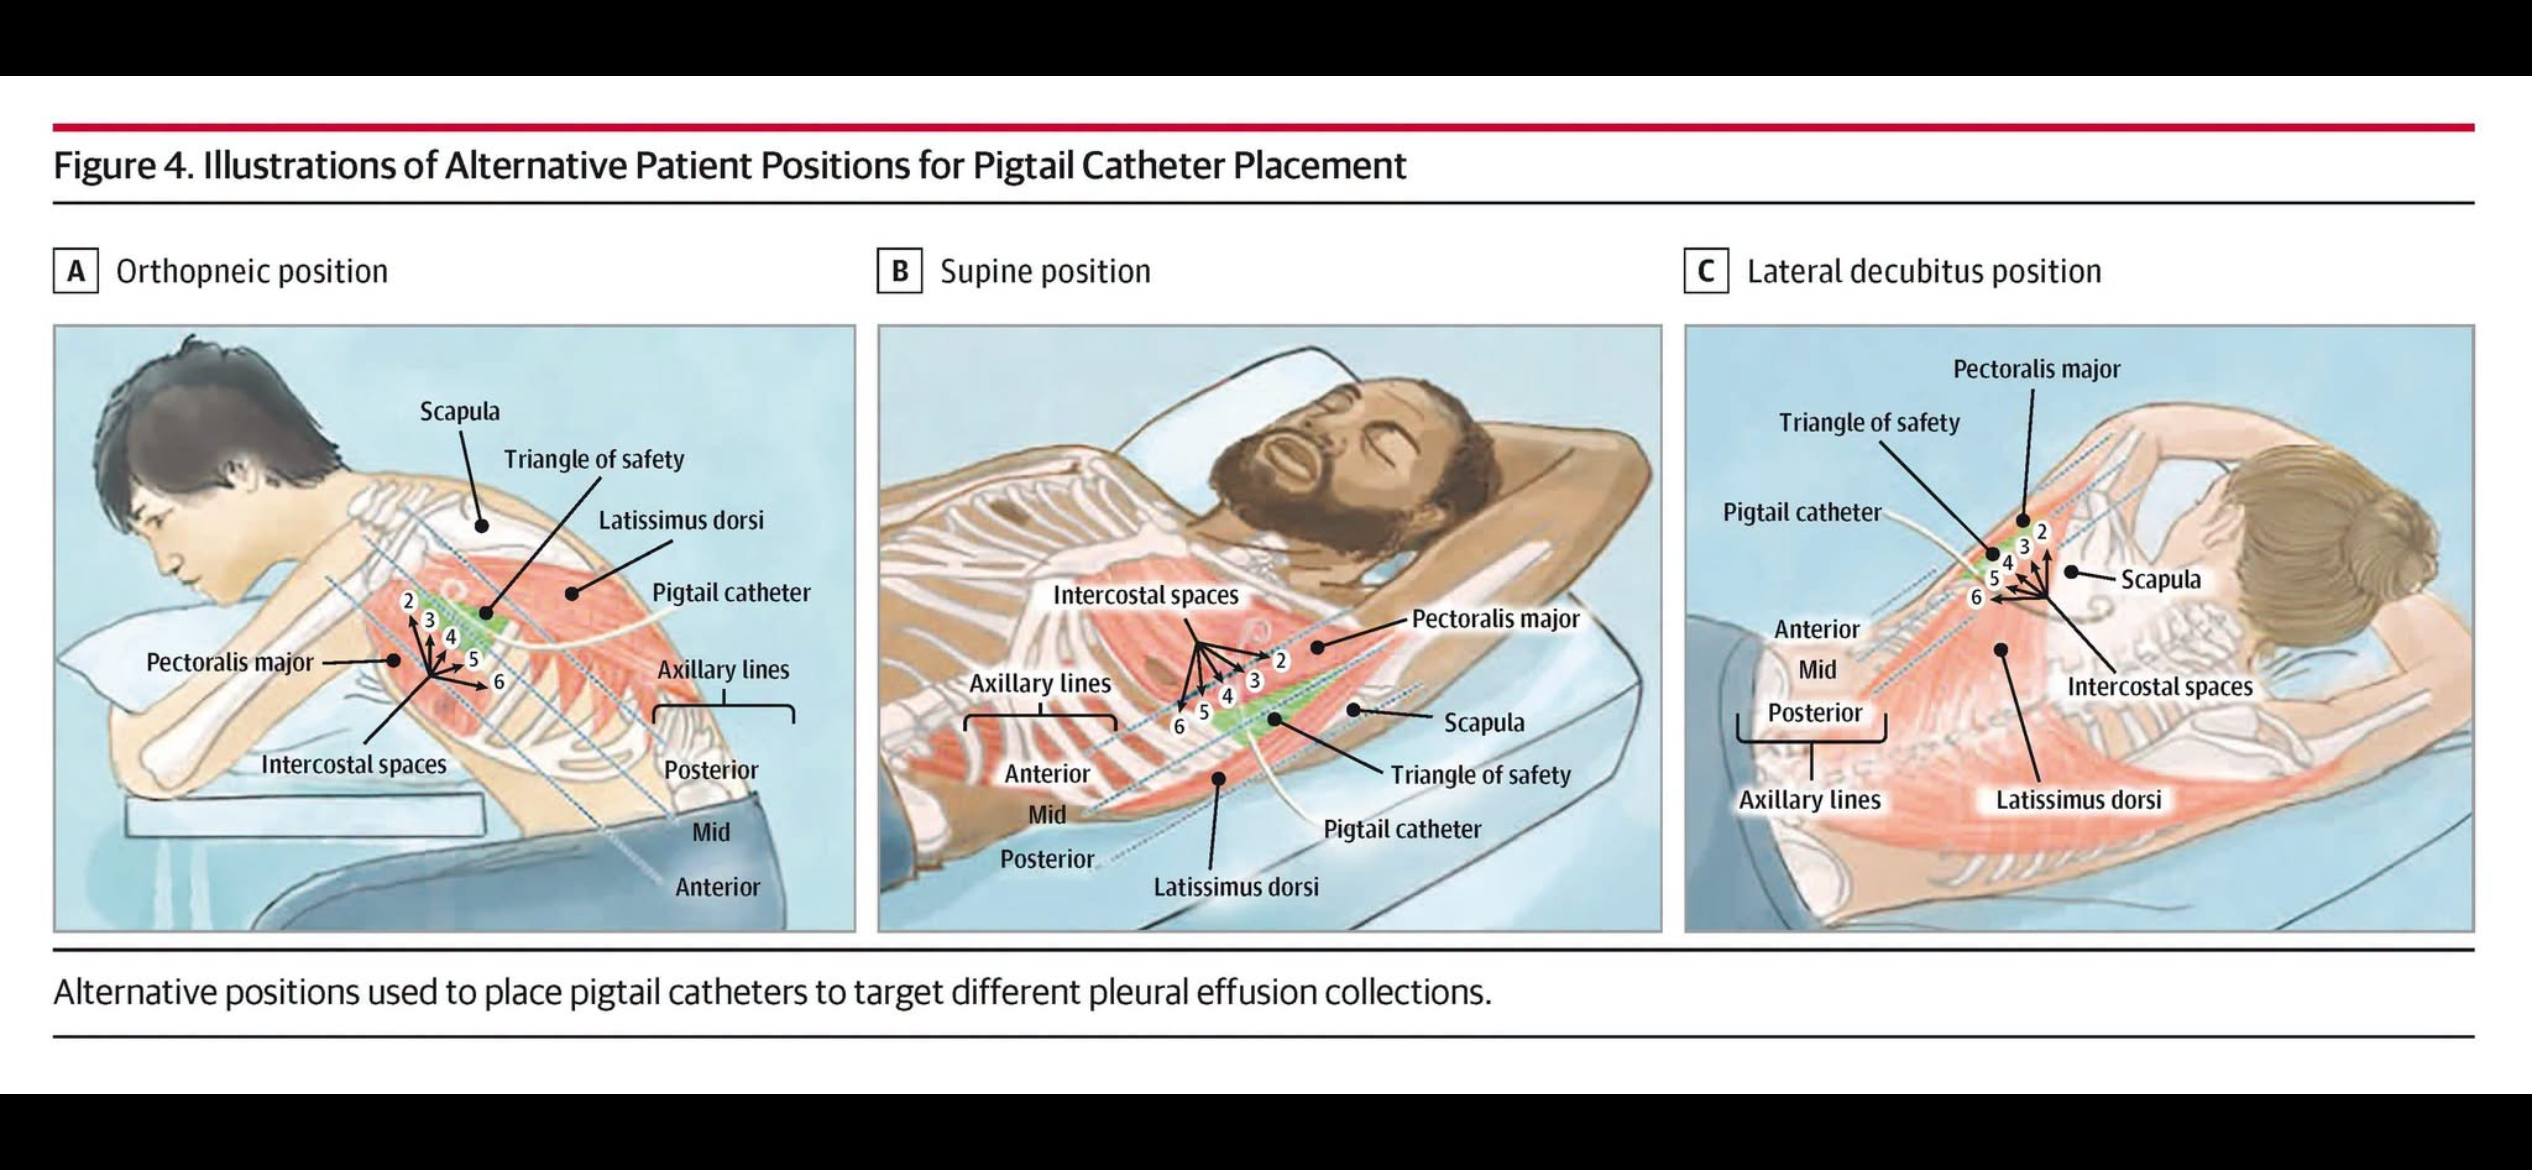
This review article reminds us that pigtail catheters can be effectively used to drain pneumothoraces, pleural effusions, hemothoraces, emphysemas, and other fluid collections within the thorax. It also offers three patient positions to use for pigtail placement.
Show References
Bottom Line:
This multicenter trial demonstrated improved physiological outcomes such as lactate clearance and renin clearance in septic shock by using early multimodal vasopressor strategy but was not powered to detect mortality benefit. Further studies looking at more patient specific outcomes with this strategy are needed.
When caring for a critically ill ICU boarder in the ED, remember to add vasopressin early for escalating norepinephrine requirements (0.2-0.3 mcg/kg/min NEE).
Show Additional Information
Show References
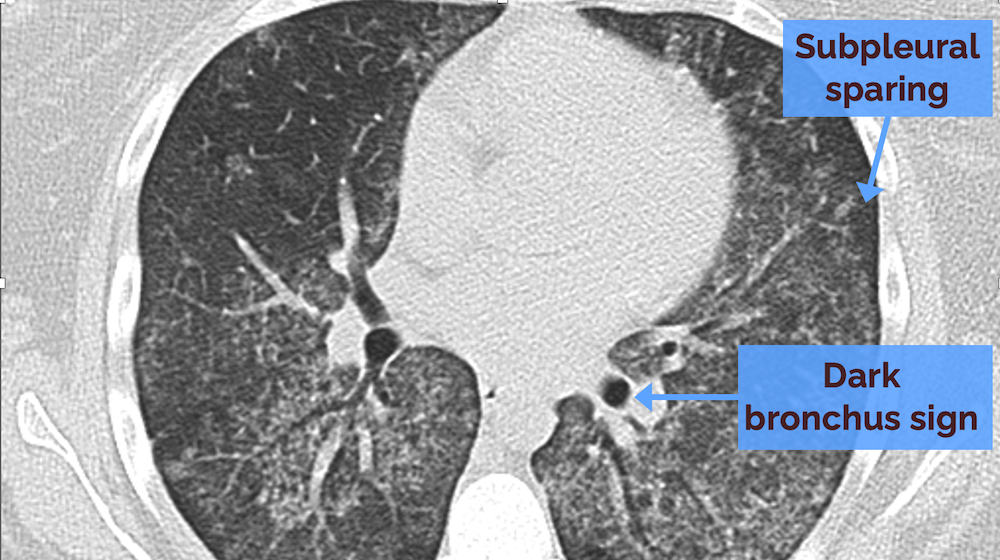
A patient presents with hypoxia, anemia, and the following CT findings:
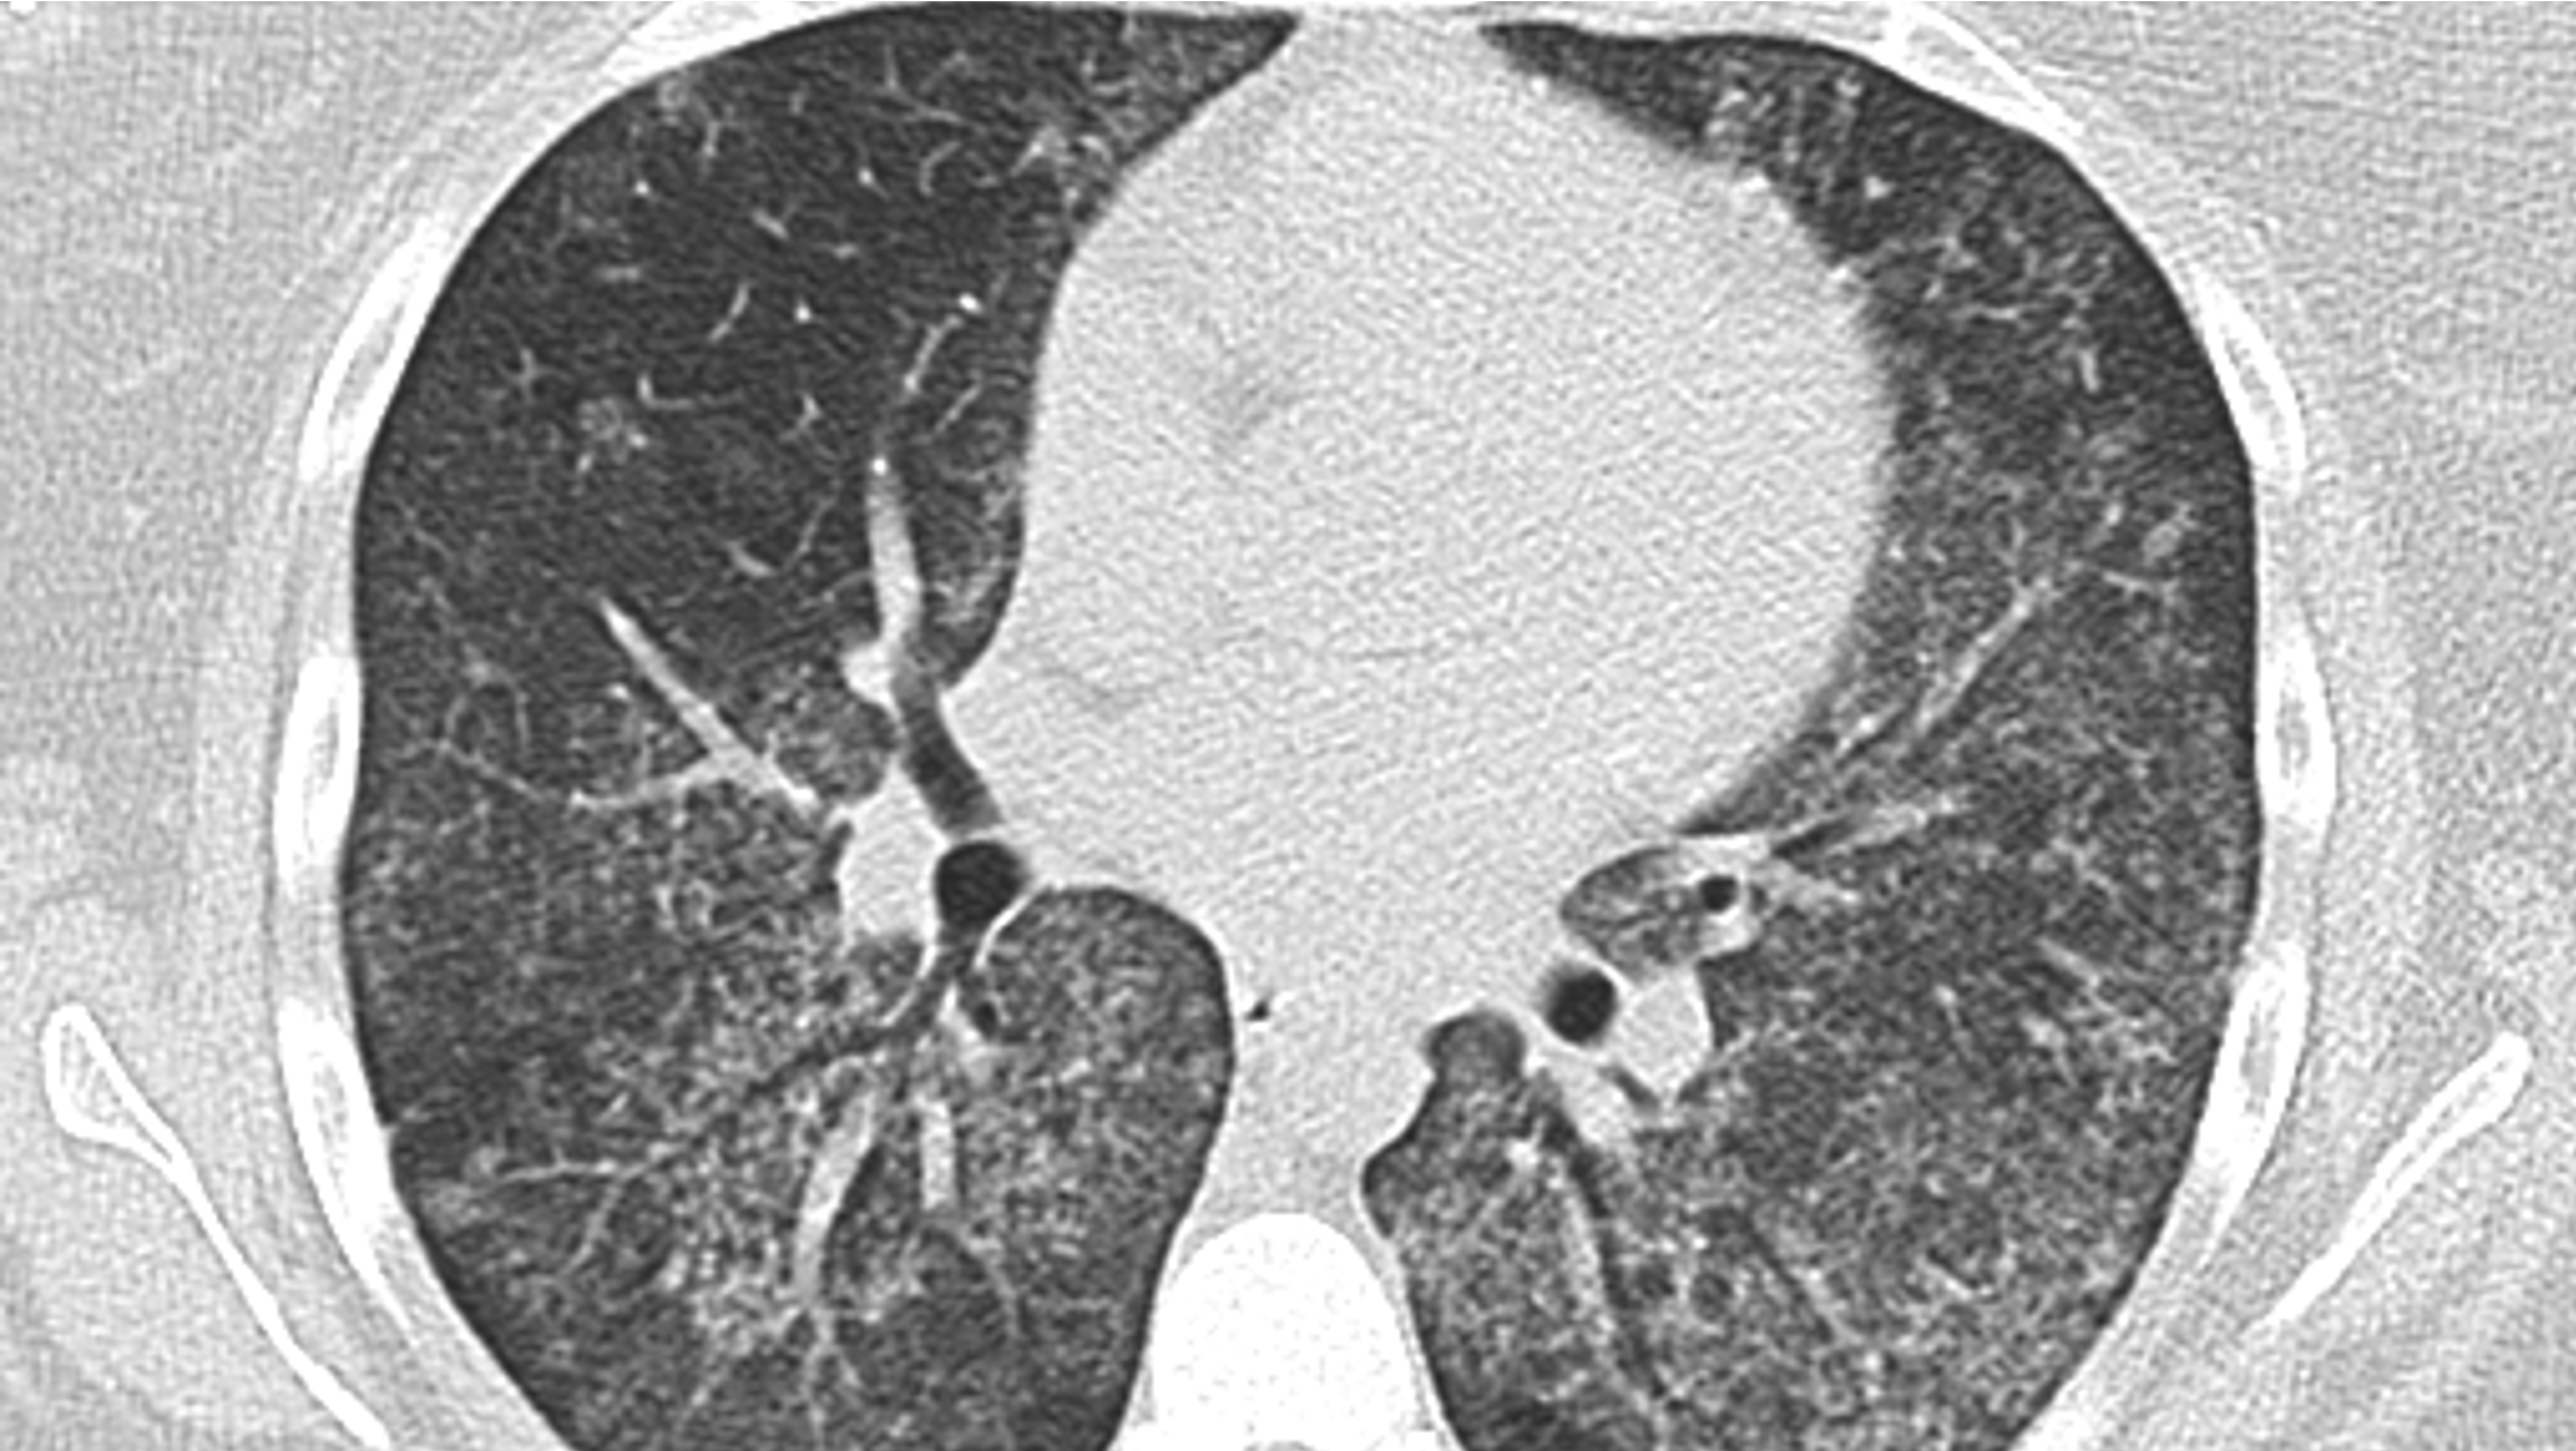
What is the diagnosis? What will you do next?
Show Additional Information
Show References
Attachments
As a reminder, age friendly health care says we should address the 4Ms with older patients; what matters, medication, mentation, and mobility.
This article says we aren’t good about discussing firearm access with older depressed patients and patients with dementia. We can do better having these conversations with our vulnerable older patients and their families.